
Key Takeaways
- Relapse often lives inside a 90-second window between trigger and action, where an emotional wave outpaces the ability to ride it without reaching for a substance.
- Emotion regulation, not improved mood, is the mechanism that drives reduced substance use in DBT — the target is handling hard feelings, not eliminating them 6.
- The four DBT modules work as a sequence: mindfulness catches the urge, distress tolerance rides the wave, emotion regulation names the feeling, and interpersonal effectiveness protects the relationships that can trigger use.
- Dialectical abstinence holds a full commitment to not using alongside an honest lapse plan, so a single slip becomes a data point instead of a full return to use 14.
The 90-Second Window Between a Trigger and a Drink
Picture the moment. You’re pulling off 77 after a long day, the truck cab quiet, and something catches you sideways — a smell, a helicopter overhead, a text from someone you haven’t heard from in months. Your chest tightens. Your jaw locks. Somewhere between that trigger and the decision to stop at the gas station for a six-pack, or to text the person you promised yourself you wouldn’t, there’s a window. It’s short. Maybe 90 seconds. And most of what determines whether you use again lives inside it.
That window is where relapse actually happens. Not in some grand failure of character. Not because you didn’t want recovery badly enough. It happens because a wave of feeling shows up faster than your ability to ride it, and the substance is the fastest tool you’ve ever had for turning the volume down. Research across 95 studies confirms what you already know in your body: difficulties with emotion regulation and substance use are tied together, with a small-to-medium effect that shows up again and again 5.
Dialectical Behavior Therapy — DBT — was built for that window. It won’t erase the trigger. It won’t pretend your deployment didn’t happen or that Ohio winters aren’t hard. What it does is hand you concrete moves to make in those 90 seconds, so that the next decision belongs to you and not to the wave. That’s the whole point of what follows.
Why Emotion Regulation Sits at the Center of Relapse
Think about the last time you nearly used, or actually did. If you rewind the tape, the story almost never starts with the substance. It starts with a feeling that got too big, too fast — grief that ambushed you in the cereal aisle, rage at a driver on 30, that hollow static that shows up around 2 a.m. when the house is finally quiet. The drink or the pill came in as a fix for the feeling. That’s the pattern DBT was built to interrupt.
A meta-analysis pulling together 95 studies found that emotion regulation difficulties and substance use are significantly related, with a small-to-medium effect that held up across populations and measures 5. That’s not one lab’s opinion. That’s a signal repeating itself across nearly a hundred research settings. When your capacity to sit with a hard feeling drops, your odds of reaching for something to blunt it climb. It’s not a character flaw. It’s a well-documented human pattern, and it’s especially loud when your nervous system has already been asked to carry more than most.
Here’s the part that matters for relapse prevention. In an early mechanistic study of DBT with people who had substance dependence and co-occurring borderline personality disorder, researchers looked at what actually drove the drop in substance use over the course of treatment. It wasn’t that participants felt happier. Improved mood, on its own, didn’t explain the change. What accounted for reduced substance use frequency was improved emotion regulation itself — the concrete ability to notice, name, and work with a feeling instead of being run by it 6. The sample was small and specific, so don’t read it as the last word. But mechanistically, it points somewhere important: the target isn’t feeling better, it’s handling feeling.
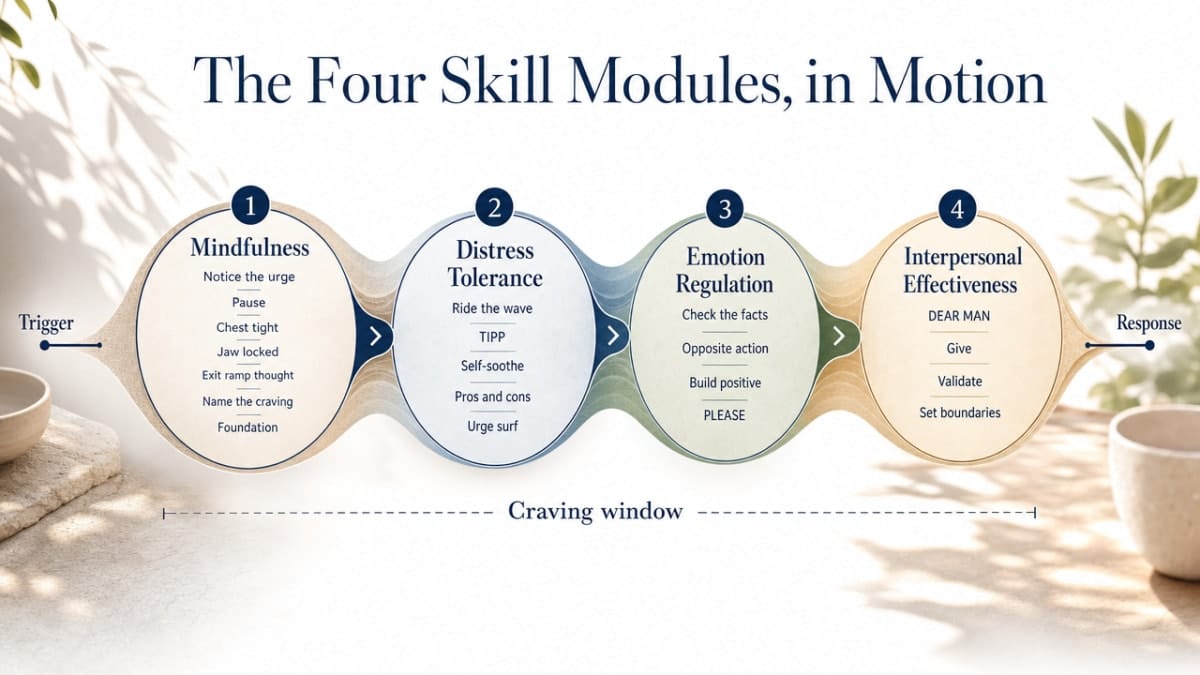
The Four Skill Modules, in Motion
Mindfulness: Noticing the Urge Before It Owns You
Mindfulness in DBT isn’t about sitting cross-legged on a cushion. It’s about catching the freight train before it’s already through the station. When you’re driving home and that helicopter noise sets off something in your chest, mindfulness is the pause where you notice — chest tight, jaw locked, hand already thinking about the exit ramp — before the story of what you’re about to do takes over.
This matters for relapse because the urge to use rarely announces itself as an urge. It shows up as a plan. Suddenly you’re rehearsing which gas station, which brand, what you’ll tell your spouse. Mindfulness slows that down enough to name what’s actually happening: this is a craving, riding on top of a feeling I haven’t looked at yet.
The 2024 mapping paper places mindfulness at the foundation of DBT’s SUD adaptation for exactly this reason — it’s the skill that makes every other skill possible, because you can’t use distress tolerance on a wave you never saw coming 14. You don’t need to be good at it to start. You just need to catch one urge one time this week and name it out loud. That counts. That’s the rep.
Distress Tolerance: Riding the Wave Without Reaching
Distress tolerance is the module that answers the honest question — okay, I noticed the urge, now what do I do with the next twenty minutes? Because cravings don’t disappear when you name them. They crest, they hold, and then, if you don’t feed them, they fall.
DBT gives you concrete moves for that stretch:
- Cold water on your face or the back of your neck to drop your heart rate.
- Paced breathing where your exhale is longer than your inhale.
- Intense exercise for a few minutes — even push-ups in the garage — to burn off the adrenaline your nervous system is dumping.
- Distracting on purpose with something that requires your hands.
These aren’t soft suggestions. They’re physiological interrupters that buy you the minutes the craving needs to pass.
The therapeutic community study from 2025 saw meaningful pre-post drops in positive urgency and sensation seeking after DBT skills training — the exact impulsivity patterns that push you from feeling to action without a pause in between 4. That’s distress tolerance doing its job. Yes, sitting with a craving without acting on it is brutal. And it’s a skill you can build one wave at a time. Each one you ride is proof the next one can be ridden too.
Emotion Regulation: Naming and Downshifting the Feeling
Once the wave has passed, the feeling underneath is still there. Emotion regulation is the work of turning toward it instead of away. What is this, really? Grief about the friend who didn’t come home. Anger at a system that made you wait months for an appointment. Shame from something you did on deployment that you’ve never said out loud.
DBT teaches you to name the feeling with precision, check whether it fits the facts of the situation, and then take one small action that shifts the intensity — sleep, food, movement, a phone call, sunlight, something you’ve been avoiding. The point isn’t to feel great. It’s to get the feeling down from a nine to a six, where you can think again.
This is the mechanism the field has flagged as central. The Axelrod mechanistic study found that improved emotion regulation — not just improved mood — accounted for the drop in substance use frequency during DBT 6. The sample was small and specific, so hold the finding loosely. But the direction is clear: you’re not chasing a better mood. You’re building the muscle that lets you carry a hard mood without a drink.
Interpersonal Effectiveness: Asking Without Blowing It Up
A lot of returns to use happen after a conversation went sideways. Your spouse doesn’t get it. Your VA rep talks past you. A family dinner in Massillon turns into the same argument you’ve been having since Thanksgiving. You leave, and the fastest way to stop feeling what you feel is the one you already know.
Interpersonal effectiveness gives you a way to ask for what you need, hold your ground, or say no — without torching the relationship or swallowing the resentment. DBT uses simple scripts for this:
- Describe the situation.
- State how you feel.
- Ask clearly for what you want.
- Reinforce why it matters.
You practice it in session and then you use it on real people, in real kitchens, on real Sunday afternoons.
The 2024 mapping paper puts interpersonal functioning alongside emotion regulation and executive function as a core clinical domain DBT targets in SUD care 14. That’s not accidental. The people you love are also the people whose words can send you toward the exit ramp fastest. Learning to have hard conversations without the fallout is relapse prevention, even when it doesn’t look like it.
Dialectical Abstinence: The Honest Middle Path
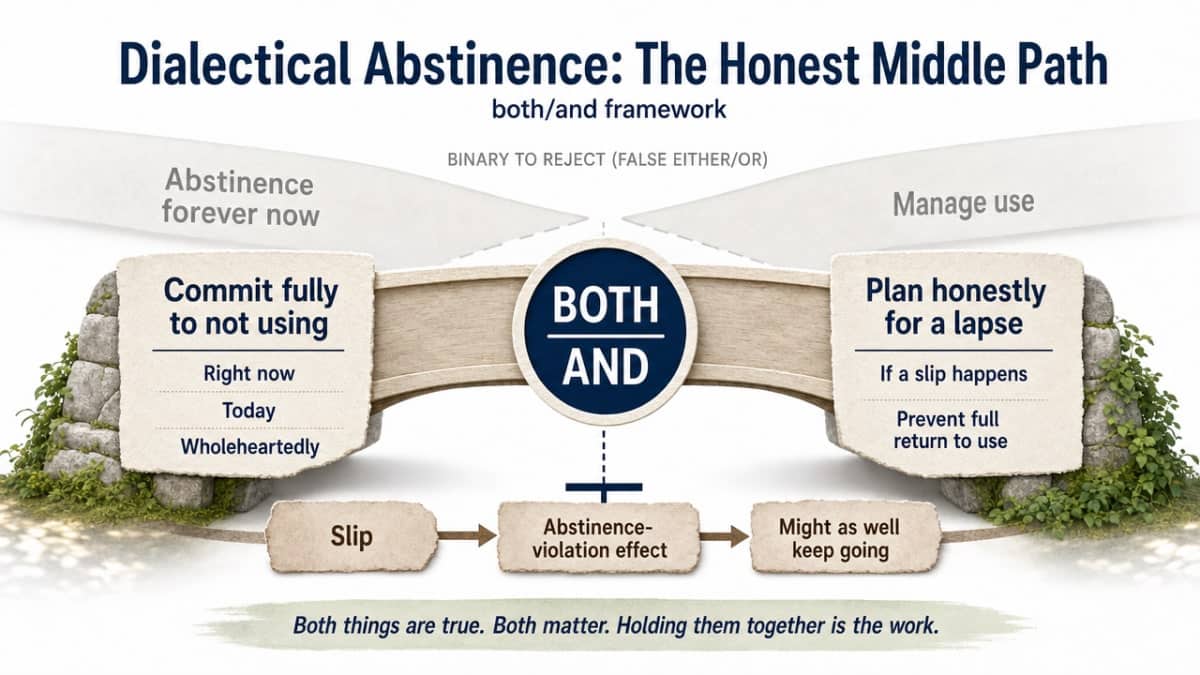
Most programs ask you to pick a lane. Either you’re all in on abstinence, forever, starting now — or you’re doing harm reduction and managing use. DBT refuses that binary, and honestly, it’s one of the more grown-up things about it.
Dialectical abstinence is the name for the both/and stance the 2024 mapping paper describes: you commit fully to not using, right now, today, with your whole chest. And at the same time, you plan honestly for the possibility of a lapse, so that if one happens, it doesn’t turn into a full return to use 14. Both things are true. Both matter. Holding them together is the work.
That second half is where a lot of people get tripped up, so it’s worth slowing down on. The abstinence-violation effect is the moment after a slip when your brain tells you the whole recovery is blown, so you might as well keep going. One beer becomes a case. One pill becomes a weekend. Dialectical abstinence teaches you, ahead of time, that a lapse is a data point, not a verdict. You know what you’ll do in the first hour after. Who you’ll call. What you’ll say to yourself instead of the shame spiral 14.
For a veteran who’s already carrying enough black-and-white thinking from years of pass/fail systems, this middle path can feel like a relief. You don’t have to be perfect to be in recovery. You have to keep coming back to the skills, one wave at a time. That’s a standard you can actually meet.
What the Evidence Actually Says (and Doesn’t)
Here’s where it’s worth slowing down. If someone tells you DBT is proven to prevent relapse across the board, they’re overselling it. The honest picture is more useful anyway.
One of the most concrete outcome signals comes from a pilot randomized trial of DBT for cannabis use disorder. At the end of treatment, 46% of the DBT group had achieved cessation compared to 16% in the control condition. At the two-month follow-up, the gap held — 40% versus 9.5% 8. Those are real numbers, and they point in a real direction. They’re also from a small pilot study with a specific substance and a short follow-up window, and the authors say so plainly. You can’t stretch a cannabis pilot into a claim about opioids or alcohol without more data.
The systematic review of DBT skills training across substance use disorders lands in a similar place. It found preliminary support for reduced substance use and improved emotion regulation, while flagging small samples, inconsistent adaptations, and mixed designs as real limits on what you can conclude 9. That’s not a red flag — it’s a fair reading of an evidence base that’s still growing.
For opioid-specific relapse prevention, which matters in Stark County and across Ohio, a field test of DBT skills inside methadone treatment found the intervention was feasible and acceptable, and the authors saw signals that it may help prevent drug relapse and increase smoke-free days. They also explicitly called for a randomized controlled trial before drawing firm conclusions 7.
So what does this mean for you, sitting with the question of whether to try another therapy? DBT has enough support to be worth your time, especially if the emotional side of relapse is where you keep getting caught. It’s not a guarantee. Nothing in this space is. What it is, is a skills-based approach with a growing evidence trail and a mechanism — emotion regulation — that lines up with what actually drives the moments you’re trying to change.
DBT for the Veteran Nervous System: Hypervigilance, Moral Injury, and Numbing
If you served, your nervous system learned things it can’t just unlearn because you’re back in Stark County now. The startle response that kept you alive downrange doesn’t check to see whether the loud noise came from an IED or from a kid slamming a car door in the Giant Eagle parking lot. Hypervigilance is a skill your body earned. It’s also exhausting to live inside of.
Here’s where a lot of substance use gets recruited. Alcohol turns the volume down on the scanning. Opioids soften the edges of the sleep that won’t come. Cannabis takes the edge off the anniversary week you didn’t even realize was coming until you were already three days into it. The substances aren’t the problem you’re trying to solve — they’re the fastest tool you found for a nervous system running hot. That framing matters, because a therapy that treats you like you’re weak-willed will fail you. DBT doesn’t do that. It treats the emotional surge as the target and gives you skills that meet the surge where it lives.
Moral injury sits alongside all of this, and it doesn’t respond well to being told to think differently. What you did, or didn’t do, or watched happen — that weight doesn’t move on a worksheet. What DBT offers is a way to carry it without needing to numb it every night. Mindfulness lets you notice the shame spiral starting. Distress tolerance gets you through the hour when the memory won’t quit. Emotion regulation helps you name it — grief, not just anger — so it stops running the show from underneath.
The impulsivity piece is worth naming plainly. The 2025 therapeutic community study saw pre-post improvements in emotion dysregulation, positive urgency, and sensation seeking after DBT skills training — the exact patterns that show up as “I don’t even remember deciding, I was just at the bar” 4. That’s a small preliminary finding, not a promise. But it lines up with what a lot of veterans describe: the gap between feeling and action shrinks after deployment, and DBT is one of the few approaches built to widen it back out.
None of this asks you to talk about deployment before you’re ready. It asks you to build the skills that make talking about it survivable when you are.
How DBT Fits Inside Integrated Care for PTSD and Substance Use
DBT isn’t meant to stand alone when trauma and substance use are traveling together. SAMHSA’s guidance on co-occurring disorders is clear that integrated care — where the mental health side and the substance use side are treated in the same plan, by teams that talk to each other — produces better relapse-prevention outcomes than treating either one in isolation 2. TIP 42 puts DBT specifically on the list of evidence-based therapies that fit inside that integrated frame, especially for people carrying emotion regulation problems and self-harm risk alongside a substance use disorder 10. That’s most veterans with PTSD and a return-to-use pattern.
What that looks like in practice is DBT skills sitting next to trauma-focused work like EMDR, not competing with it. DBT builds the emotional shock absorbers first — mindfulness, distress tolerance, regulation — so that when you do open up the deployment memory in EMDR or trauma-focused CBT, you have somewhere to land after. Medication-assisted treatment for opioid or alcohol use disorder can run in parallel. Group work, family sessions, and aftercare planning stack on top.
The piece that gets underestimated is retention. In a randomized controlled trial of DBT for women with concurrent eating disorders and substance use disorders, 80% of the DBT group stayed in treatment through post-treatment compared to 20% in treatment-as-usual, and at follow-up the gap was 60% versus 20% 12. That’s a specific dual-diagnosis sample, not a promise about every population — the study was small and gender-specific. But it points at something real: relapse-prevention skills only work if you’re still in the room to learn them, and DBT seems to help people stay in the room.

What a DBT-Informed Plan Looks Like in Residential and IOP
A DBT-informed plan isn’t a worksheet packet handed to you at intake. It’s a shape your week takes, and that shape shifts depending on where you are in care. In residential — the deepest end of the continuum — the days are built to protect your nervous system while you learn the skills. Mornings might hold a skills group where you actually rehearse distress tolerance moves out loud, not just read about them. Afternoons make room for one-on-one work with a therapist who knows your file, plus space for trauma-focused therapy like EMDR when you’re steady enough to open it. Medication-assisted treatment, if it fits your situation, runs alongside — not instead.
Step down to partial hospitalization or IOP and the same pieces are there, just spread across fewer hours. You might come in three evenings a week after work, hit a skills group, meet with your counselor, and take the drive back to Massillon or up 77 to Cleveland with homework you’ll actually use before the next session. That between-session practice is where DBT lives. The 2024 mapping paper makes the case plainly: skills like dialectical abstinence, mindfulness, and lapse planning only translate to relapse prevention when they’re rehearsed in the settings where cravings actually show up — the kitchen at 10 p.m., the drive past the old bar, the group text that always sets you off 14. Outpatient and aftercare keep the reps going once the schedule loosens. That’s the whole arc — skills built in a safe room, practiced in your real one.
A Confidential Next Step in Massillon or Cleveland
If you’ve read this far, something in it landed. Maybe the 90-second window. Maybe the part about hypervigilance not being a character flaw. Whatever it was, you don’t have to figure out the next step alone.
Arrow Passage Recovery works with veterans across Ohio from our locations in Massillon and Cleveland. DBT lives inside a personalized plan alongside EMDR, medication-assisted treatment, and dual-diagnosis care — whatever your situation actually needs, at whatever level of the continuum fits, from residential through aftercare. Most major insurance is accepted, including Tricare.
A call is a call. It’s confidential, there’s no pressure, and you can ask the hard questions before you decide anything. When you’re ready, we’re here.
Start Your Path to Safer, Lasting Recovery
Connect one-on-one to privately explore your best options for relapse prevention and support.
Frequently Asked Questions
Is DBT different from the CBT I already tried through the VA?
Yes, in a specific way. CBT works mostly on the thoughts underneath the feeling. DBT works on the feeling itself, in the body, in real time — plus the thoughts. If CBT didn’t stick, it’s often because the wave was already breaking before you could think your way through it. DBT hands you skills for the wave 14.
Can DBT work if I have PTSD and a substance use disorder together?
That’s actually where it tends to fit best. SAMHSA’s TIP 42 names DBT as evidence-based for people carrying emotion regulation problems and self-harm risk alongside a substance use disorder 10. Integrated care that pairs DBT skills with trauma-focused work like EMDR is the model that lines up with what most veterans with PTSD and a return-to-use pattern actually need 2.
What is dialectical abstinence, and does it mean I can keep using sometimes?
No. Dialectical abstinence means you commit fully to not using, right now, today — and you plan honestly for what you’d do if a lapse happened, so it doesn’t cascade into a full return to use 14. Both halves matter. The commitment is real. The lapse plan is a safety net, not a permission slip.
How long does it take before DBT skills actually help with cravings?
Some skills — cold water, paced breathing, naming the feeling — can help the first week you try them. Deeper change in emotion regulation builds over months of practice. The cannabis pilot showed meaningful cessation differences by end of treatment and held at two-month follow-up 8. Progress is real and gradual. One ridden wave counts.
Do I need residential treatment, or can DBT work in an IOP schedule?
Both can work. Residential protects your nervous system while you learn the skills. IOP lets you practice them in your actual life — the kitchen at 10 p.m., the drive up 77 — with weekly reps and a counselor who knows your file. What matters most is that the skills get rehearsed where cravings actually show up 14.
What happens if I have a lapse during DBT treatment?
You come back. That’s the whole design. A lapse is treated as a data point about what triggered it and which skill didn’t reach you in time — not as proof you failed. The abstinence-violation effect is what DBT is built to interrupt, so one slip doesn’t become a weekend 14. Call your counselor. Keep going.
References
- Dialectical Behavior Therapy for Substance Abusers. https://pmc.ncbi.nlm.nih.gov/articles/PMC2797106/
- Substance Use Disorder Treatment for People With Co-Occurring Disorders. https://library.samhsa.gov/sites/default/files/pep20-06-04-006.pdf
- Predictors of Treatment Outcome and Engagement in Self-Guided Internet-Delivered Dialectical Behavior Therapy for Substance Use Disorders. https://pubmed.ncbi.nlm.nih.gov/40524389/
- The Therapeutic Community Integrated With a DBT Skills Training Program for Substance Use Disorders: The Initial Efficacy for the Treatment of Impulsivity and Related Dimensions. https://pubmed.ncbi.nlm.nih.gov/40215471/
- Emotion Regulation and Substance Use: A Meta-Analysis. https://pmc.ncbi.nlm.nih.gov/articles/PMC8714680/
- Emotion regulation and substance use frequency in women with substance dependence and borderline personality disorder receiving dialectical behavior therapy. https://pubmed.ncbi.nlm.nih.gov/21091162/
- Field Test of a Dialectical Behavior Therapy Skills Training-Based Intervention for Smoking Cessation and Opioid Relapse Prevention in Methadone Treatment. https://pubmed.ncbi.nlm.nih.gov/30646819/
- A pilot randomized controlled trial of dialectical behavior therapy for cannabis use disorder. https://pmc.ncbi.nlm.nih.gov/articles/PMC8835386/
- Dialectical behaviour therapy skills training for individuals with substance use disorders: A systematic review. https://pubmed.ncbi.nlm.nih.gov/34337811/
- Substance Abuse Treatment for Persons with Co-Occurring Disorders (TIP 42). https://store.samhsa.gov/sites/default/files/d7/priv/sma13-4793.pdf
- A randomized controlled trial of an Internet delivered dialectical behavior therapy skills training for suicidal and heavy episodic drinkers. https://pmc.ncbi.nlm.nih.gov/articles/PMC5859943/
- Outcome of dialectical behaviour therapy for concurrent eating and substance use disorders. https://pubmed.ncbi.nlm.nih.gov/21416557/
- Feasibility, Acceptability, and Potential Efficacy of a Self-Guided Internet-Delivered Dialectical Behavior Therapy Intervention for Substance Use Disorders: Randomized Controlled Trial. https://pmc.ncbi.nlm.nih.gov/articles/PMC10828941/
- Mapping Dialectical Behavior Therapy Skills to Clinical Domains and Targets in Substance Use Disorder Treatment. https://pmc.ncbi.nlm.nih.gov/articles/PMC12334178/
